It is not one number. Pocket depths, bleeding, gum attachment and x-rays are read together. You are entitled to see the chart.
Share:
Summary:
The short answer, before anything else
A deep cleaning is recommended on the basis of a periodontal assessment, not one number. Your dentist or hygienist measures the space between tooth and gum at several points per tooth, notes where the gums bleed when probed, looks at whether the gum has pulled away from the tooth, reviews your medical history, and takes x-rays to check the supporting bone. NIDCR describes healthy pockets as usually 1 to 3 millimeters and notes that deeper pockets can indicate periodontal disease.
Those findings are read together. The same depth reading can mean different things depending on whether the site bleeds, whether bone has been lost, and what the rest of your mouth looks like.
Ask to see your chart. You are entitled to have the numbers read out and explained, and to have the reasoning behind the recommendation set out tooth by tooth.
You booked twenty minutes and a new toothbrush. Instead someone is talking about scaling, root planing and a second appointment. That is a reasonable thing to want explained, so here is what sits behind the recommendation.
Between every tooth and the gum around it there is a small natural space. Its depth is measured with a thin probe marked in millimeters, at several points per tooth. That measurement is one input among several.
What a periodontal assessment takes into account
Depth is one finding among several, and no single row decides the recommendation on its own.
| What is assessed | Why it matters |
|---|---|
| Pocket depth around each tooth | NIDCR describes healthy pockets as usually 1 to 3 millimeters. Deeper pockets can indicate periodontal disease |
| Bleeding when the site is probed | A sign of active inflammation at that specific site |
| Whether the gum has pulled away from the tooth | NIDCR lists gums pulling away from teeth among the signs of gum disease |
| X-rays of the supporting bone | NIDCR lists x-rays to check for bone loss as part of diagnosis |
| Your medical history and risk factors | NIDCR names smoking or tobacco use as the most significant risk factor, and also lists diabetes, age, genetics, stress, some illnesses, obesity, some medications and hormonal changes |
| How the picture compares with earlier records | Shows whether a finding is new or long-standing |
A reading of 4 millimeters at a site that does not bleed, with no bone loss on the x-ray, is a different situation from 4 millimeters that bleeds at a site where the x-ray shows bone has been lost. That is why the assessment is read as a whole, and why your dentist should be able to explain which findings are driving the recommendation for your mouth.
Knowing your own numbers makes the conversation easier. Ask for them at every visit.
They are not a small version and a large version of the same thing.
| Regular cleaning | Deep cleaning, also called scaling and root planing | |
|---|---|---|
| Where it works | At and just above the gum line, on surfaces that can be reached | Below the gum line, on the root surface inside the pocket |
| What it is for | Routine preventive care | NIDCR describes it as a deep cleaning of the affected tooth, used in treating gum disease |
| Who performs it | A dentist or hygienist | NIDCR says a dentist or hygienist |
| Appointments | Usually one | Often more than one, working on part of the mouth at a time |
| Numbing | Not usually needed | Local anesthetic is commonly used for the area being treated |
If deeper pockets and active disease are present, a regular cleaning does not reach the root surfaces inside those pockets, which is the reason the recommendation changes.
People reasonably ask what is different, since they have had cleanings for years without this conversation. A few things can be going on.
Want live answers?
Connect with a Scott Kupetz expert for fast, friendly support.
You are free to decline or to take time to think, and cost is a common and reasonable reason.
NIDCR describes gum disease as an infection that causes inflammation of the tissues holding the teeth in place, and says that in advanced disease the bone supporting the teeth is destroyed. It also lists loose teeth among the symptoms. Deposits below the gum line are not reached by brushing and flossing, so the usual expectation is that an untreated pocket does not resolve on its own.
Worth knowing: NIDCR describes early gum disease caused by plaque buildup as often reversible with daily brushing and flossing. Once bone has been lost, treatment focuses on controlling the infection rather than rebuilding what has gone. That is the reason this is usually a conversation about acting sooner rather than later.
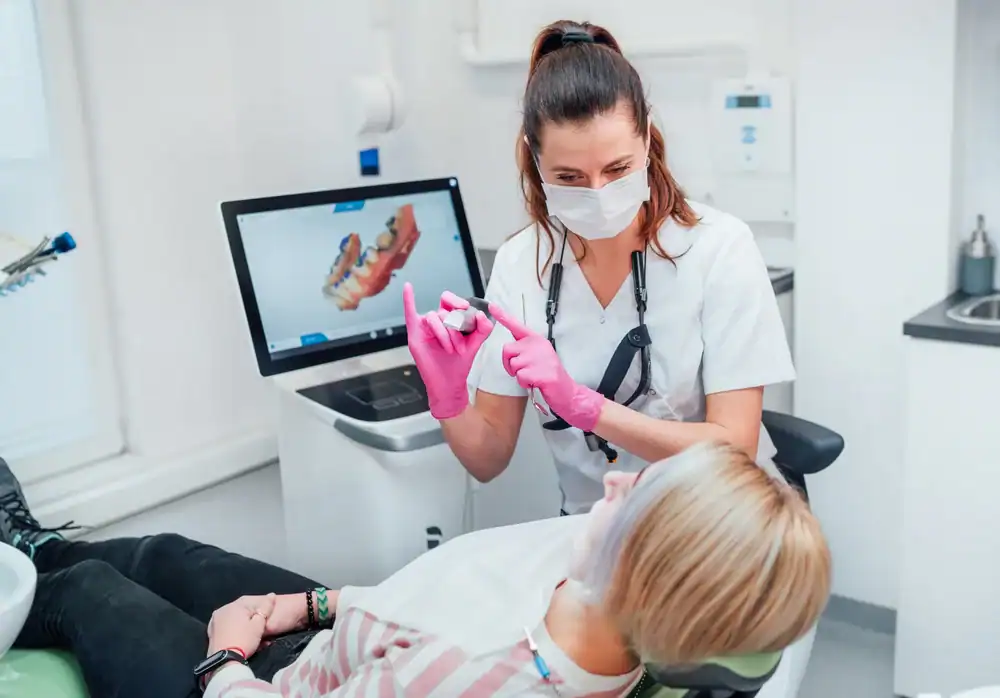
With the area numbed with local anesthetic, most people describe the procedure as tedious rather than painful. You will hear the ultrasonic scaler and feel pressure and water. Working in sections rather than the whole mouth at once is common, and it is one reason the treatment is often split across appointments.
Afterwards, tender gums and increased sensitivity to cold are common for a period, and usually settle. Some people notice their teeth look slightly longer afterwards, because swollen gum tissue has settled as the inflammation resolves.
How much any individual experiences varies, so ask your dentist what to expect in your case rather than working from a general description.
If anxiety rather than cost is the obstacle, say so when you book so the appointment can be planned around it.
After treatment, the same points are re-measured to see how the tissue has responded. That comparison is how you find out whether the treatment achieved what it was meant to. Your dentist will tell you the interval they want for your case.
If some sites have not responded, that is useful information rather than a failure, and it shows which teeth need more attention. Occasionally a site needs more than scaling and root planing can achieve, and NIDCR notes that advanced cases may require surgical treatment. NIDCR also says a referral to a periodontist, a gum disease specialist, may be recommended. You can read more about general and gum care at both of our offices.
NIDCR is clear that daily home care is required after any treatment, and that quitting tobacco can improve the results. Those are the parts that continue after you leave.
If you are holding a treatment plan you were not expecting, come in and ask to be shown the chart. We will go through the pocket depths tooth by tooth, point out which findings are driving the recommendation, and say plainly where the picture is borderline.
Dutchess and Ulster County
260 New Hackensack Road
Wappingers Falls, NY 12590
Albany, Rensselaer and Schenectady
1221 Curry Road
Rotterdam, NY 12306
Call 845-431-9115 and ask for a periodontal assessment. We accept CareCredit if spreading the cost helps.
Article details:
Share:
Continue learning: